
Phalloplasty creates a penis for trans men and transmasculine people, using a flap of skin and tissue from another part of the body, such as the thigh, forearm, groin or back. Blood vessels and nerves in the flap are connected to those in the groin using microsurgery, so the new penis has a blood supply and can develop sensation.
For many trans men, phalloplasty is the final step of genital transition, after top surgery, hysterectomy and vaginal closure (vaginectomy). After surgery, many patients can:
- Stand to urinate, if the urethra is lengthened
- Have penetrative sex, with the help of a penile implant
- No longer menstruate, once a hysterectomy has been performed
Phalloplasty creates a larger penis than metoidioplasty, which uses the clitoris enlarged by testosterone. However, it’s more complex and is usually done in several stages.
What to Expect During and After Surgery
Phalloplasty uses skin flaps (donor tissue) to create a penis and urethra. These flaps are taken from specific parts of the body, such as the forearm, thigh, or back.
Risks include:
- Infection, bleeding, or scarring.
- Complications with skin flaps, like poor healing or unsatisfactory appearance.
- Nerve or blood vessel damage, potentially reducing sensitivity or blood flow.
After surgery, patients must closely follow their surgeon’s instructions to minimize risks and promote healing. This includes taking prescribed medications, keeping incisions clean, and avoiding strenuous activities. Physical therapy may also help with functionality.
Goals of Phalloplasty
- Appearance: a penis with a natural size and shape.
- Urination: the ability to stand to urinate, with the urethra extended to the tip (if chosen).
- Sensation: sexual sensation, through nerve connections.
- Sexual function: penetrative sex, with a penile implant.
- Minimal scarring: at the donor site and genitals.
Who is Eligible for Phalloplasty?
- Age: At least 20 years old (parental or guardian consent required for those under 20; surgery is not recommended for anyone under 18).
- Hormone Therapy: At least one year of testosterone treatment.
- Living as a Man: For at least one year.
- Mental Health Clearance: A psychiatric evaluation confirming mental stability.
- Physical Health: Non-obese and physically fit.
- Previous Surgeries: Completed mastectomy and hysterectomy/oophorectomy at least six months before phalloplasty.

Dr. Kamol Pansritum and His Team
Since 1997, Dr Kamol has performed over 10,000 procedures on transgender patients and over 5,000 sex reassignment surgeries (SRS). Recognized and respected throughout the medical community as one of the most experienced surgeons working in gender reassignment surgery in the world, Dr. Kamol currently performs more than 500 male-to-female sex reassignment surgeries and more than 300 female-to-male surgeries each year. He is the chief plastic surgeon at Kamol Cosmetic Hospital in Bangkok, Thailand, where he leads the team in male-to-female and female-to-male sex transitions and face feminization.
Phalloplasty Techniques at Kamol Hospital
Kamol Cosmetic Hospital offers the options for phalloplasty as follows:
1. Anterolateral Thigh (ALT) Phalloplasty
Skin and tissue from the outer thigh are used to create the penis. The donor site is covered with a skin graft from the other thigh. Options include:
- Full phalloplasty with urethral lengthening
- Phalloplasty after a previous metoidioplasty
- Phalloplasty without urethral lengthening (a simpler operation; you continue to urinate sitting down)
When the urethra is lengthened, it’s usually built in advance (urethral prefabrication): a tube is placed in the thigh 3–6 months before the main surgery, so it can heal and become part of the flap. This reduces the risk of narrowing at the join between the old and new urethra.
- Advantages: a larger penis (about 13–14 cm), a donor scar that can be hidden by clothing, and enough bulk to hold a penile implant well
- Limitations: may be too bulky in patients with thick thigh fat, and a penile implant is still needed for penetration
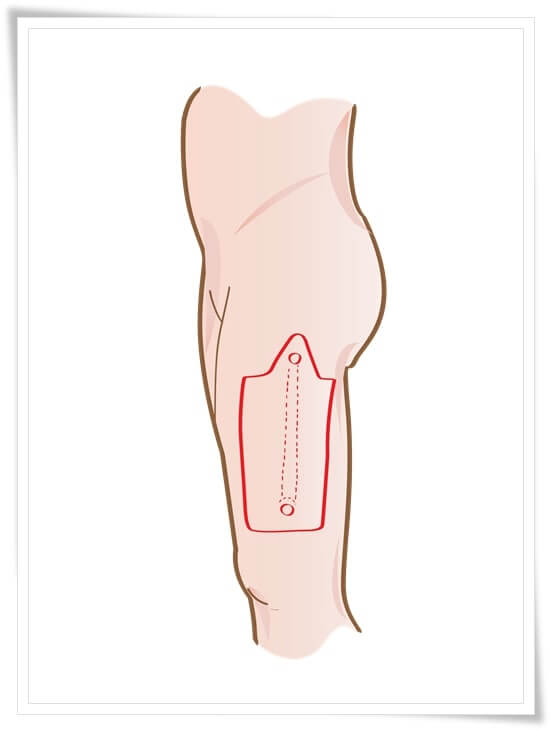
Picture 1: ALT-Pedicle Flap Phalloplasty
2. SCIP Flap Phalloplasty
A flap of skin from the groin (superficial circumflex iliac perforator flap) is used to create the penis.
- Advantages: a discreet donor scar and a relatively hairless donor area
- Limitations: a smaller penis (about 10–12 cm) and fair sensation
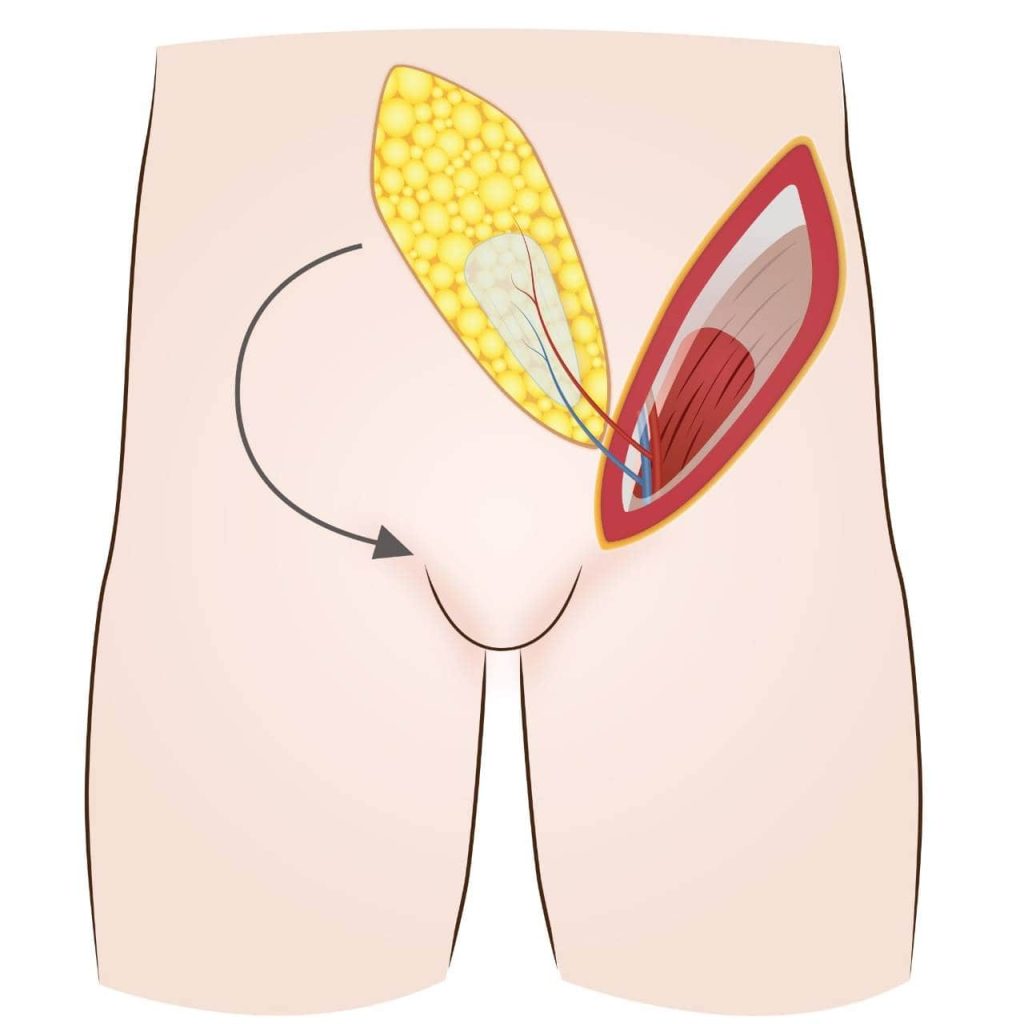
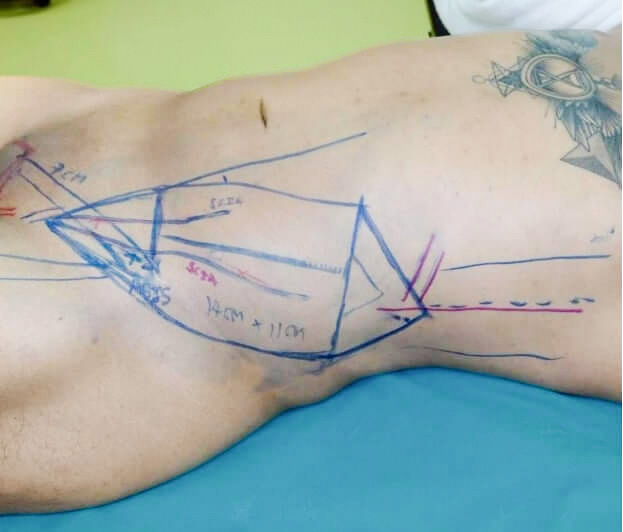
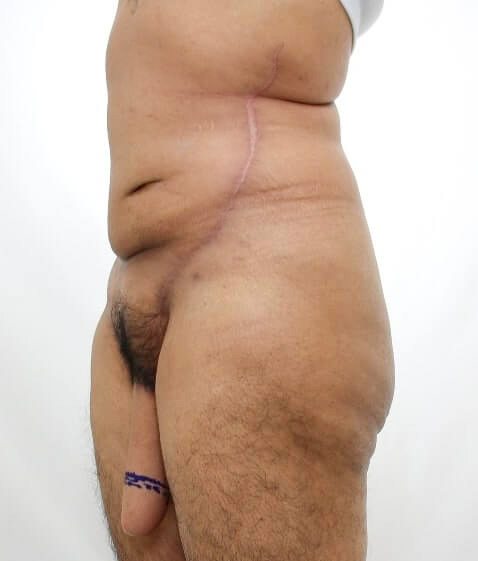
Picture 4: SCIP Phalloplasty
3. Radial Forearm Free Flap (RFFF) Phalloplasty
Skin from the inner forearm is used to create the penis using microsurgery. There are two approaches:
- Two-stage technique: the urethra is prefabricated in the forearm about 6 months before the main surgery. Suitable if the mid-forearm circumference is less than 20 cm.
- One-stage technique: the penis and urethra are built in one operation. Suitable if the mid-forearm circumference is more than 20 cm.
- Advantages: thin skin for good appearance, a medium-sized penis (about 11–13 cm), good sensation, and blood vessels and nerves that are straightforward to connect
- Limitations: a visible forearm scar, possible hand sensitivity issues, and because the penis is thinner, a higher risk of implant problems such as erosion
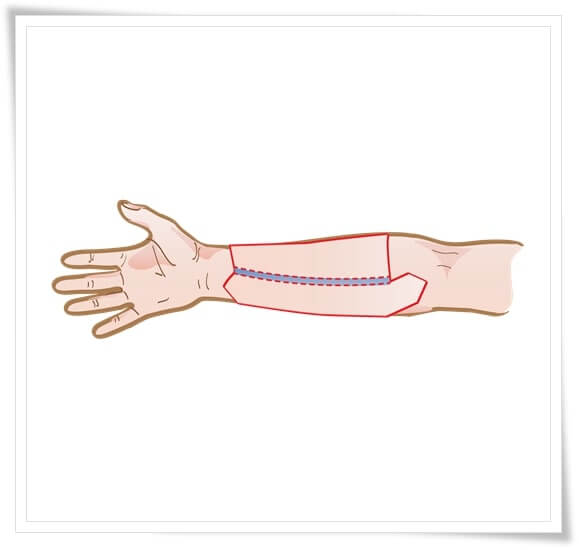
4. Musculocutaneous Latissimus Dorsi (MLD) Flap Phalloplasty
Skin and muscle from the back are used to create the penis.
- Advantages: the scar is on the torso, the donor site is hairless, and the appearance is good
- Limitations: less sensation, a second operation needed for the urethra, and the risks of microsurgery
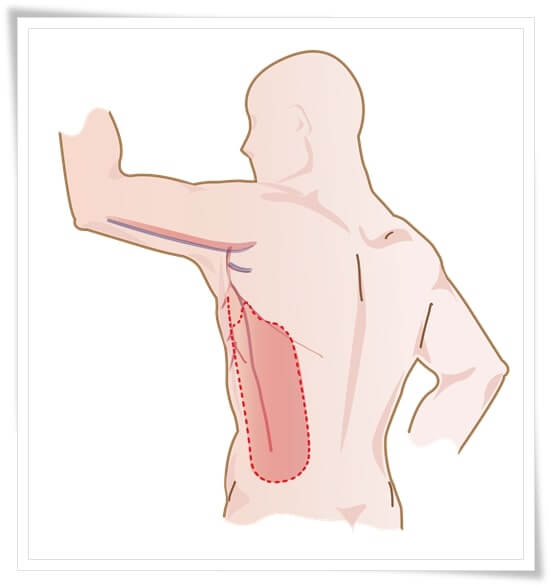
5. Fibula Flap Phalloplasty
Building a new urethra carries a relatively high risk of complications, such as a leak (fistula) or narrowing (stricture). A shorter new urethra generally has fewer complications. You can choose:
- No urethral lengthening (sitting urination): no risk of urethral complications. With ALT, healing takes about 1 month.
- Partial lengthening (standing urination from the base of the penis): a lower risk of complications.
- Full lengthening (urination from the tip of the penis): the highest risk of complications.
Preparing the Donor Site
For ALT phalloplasty:
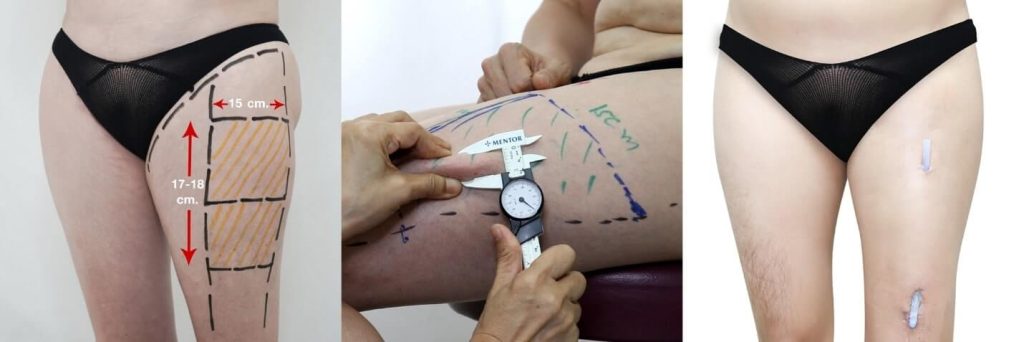
- An area of about 15 × 18 cm on one thigh is marked.
- Hair in that area is removed completely, so hair doesn’t grow on the penis.
- Skin thickness is checked by pinching. It should be less than about 1.5–1.8 cm
[CONFIRM: the Thai page states 2 cm for phalloplasty without urethra]. If it’s thicker, liposuction is performed first, followed by a wait of 6–8 months for the area to soften. If urethral prefabrication is needed, the tube can be placed 2–3 months after liposuction.
In some cases, a skin expander may be used beforehand to create extra skin, which takes 1–2 months of preparation.
Neo-urethra Reconstruction
The risks and complications associated with neo-urethra reconstruction, such as urethral stricture and fistula, are generally high. However, shorter urethras tend to have fewer complications. For individuals concerned about urethral complications, the following options are available:
- Phalloplasty without urethral reconstruction (sitting urination): No risk of urethral complications.
- Partial urethral reconstruction (standing urination from the base of the penis): Lower risk of complications.
- Full urethral reconstruction (urination from the tip of the penis): Higher risk of complications.
Preparation
- Consult the plastic surgeon about goals, health conditions, current medication and surgical options. Have a physical examination, blood tests and chest X-ray.
- Be assessed by at least two psychiatrists.
- Be in good health for surgery and general anesthesia, with a BMI under 24.
- Take testosterone for at least 1 year.
- Stop hormones for at least 2 weeks before surgery.
- Stop smoking and alcohol for at least 2 weeks before surgery.
- Stop medicines and supplements that affect blood clotting, such as aspirin and vitamin E.
- Plan time off work and prepare for wound care after surgery.
Surgical Stages
Phalloplasty is usually done in stages, with at least 3–6 months between each to allow healing:
- Hysterectomy, vaginectomy and initial urethral lengthening: the uterus and ovaries are removed, the vagina is closed, and the urethra is moved up to the pubic area using vaginal tissue.
- Urethral prefabrication (if needed): a tube is placed in the donor site 3–6 months in advance.
- Phalloplasty: the flap is transferred with microsurgery, blood vessels and nerves are connected, and the urethra is joined.
- Catheter removal: after about 3 weeks, you can begin to urinate through the new penis.
- Final stages: shaping the tip of the penis (glansplasty), testicular implants placed in the labia majora, and, after about 1–2 years once nerves have recovered, a penile implant.
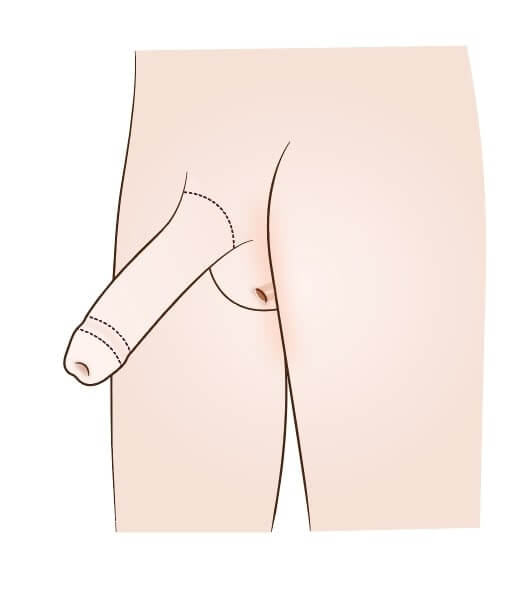
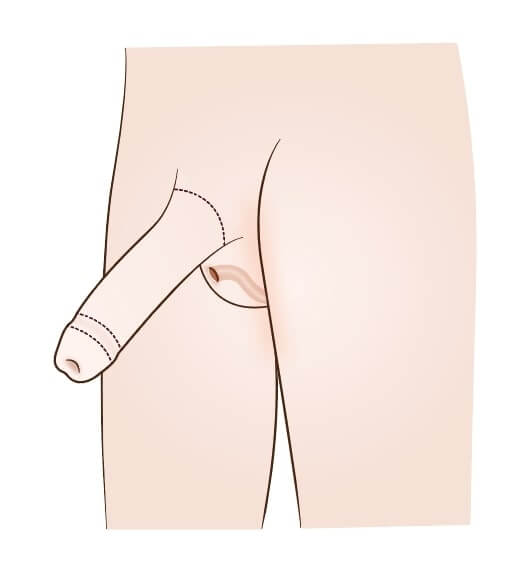
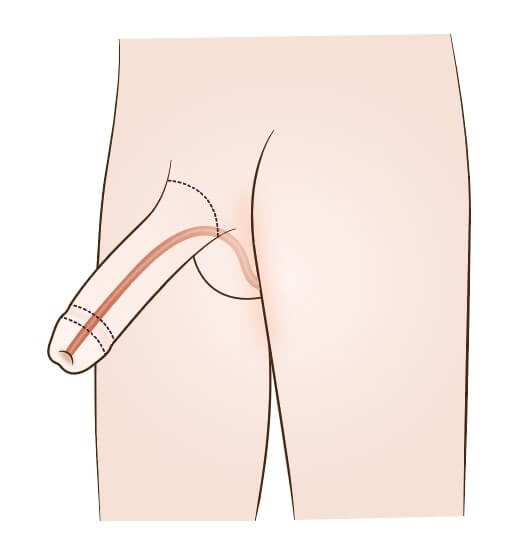
Post-operative Care
- Avoid any pressure on the new penis, which can reduce its blood supply.
- Keep the new penis raised and upright at all times to reduce swelling.
- Don’t apply ice, as cold reduces blood flow to the flap.
- Your wound is cleaned daily by our specialist nurses for 2–3 weeks.
- Keep the urinary catheter secure as instructed, and empty the urine bag often.
- Itching, swelling, some blood in the urine bag, constipation and nausea are normal in the first 1–2 weeks.
Recovery
- Catheter: stays in for about 2–3 weeks. Once it’s removed, you’ll start urinating through the new penis (if the urethra was lengthened).
- Exercise and lifting: walk slowly, and avoid exercise and lifting during early recovery.
- Work: most patients return after 6–8 weeks.
- Sensation: nerve connections take at least 6 months, and up to 2 years, to recover.
Risks and Complications
Phalloplasty carries potential risks, including:
- Urethral complications: a leak (fistula) or narrowing (stricture), which may need further surgery
- Flap loss: reduced blood supply to the transferred tissue can cause partial or complete loss, needing further surgery
- Skin necrosis at the graft
- Wound separation or delayed healing
- Bleeding and infection
- Pain, swelling and bruising
- Reduced or lost sensation
- Donor site scarring
- Dissatisfaction with the result, possibly needing revision
Why Choose Kamol Hospital in Bangkok for Phalloplasty
- Microsurgery expertise: Our team connects blood vessels and nerves under the microscope, which is essential for the flap to survive and develop sensation.
- Several donor sites: ALT, SCIP, radial forearm and MLD flaps, so the technique can be matched to your body and priorities.
- Urethral options that fit your goals: Full, partial or no urethral lengthening, with prefabrication to reduce complications.
- All stages under one roof: Top surgery, hysterectomy, phalloplasty, glansplasty, and testicular and penile implants, planned as one pathway.
- Specialist wound care: Daily wound care by nurses experienced in gender-affirming surgery until the flap has healed.
- Hospital-level safety: General anesthesia with a dedicated anesthesia team, in a JCI-accredited hospital.
- Support for international patients: Multilingual coordinators and Kamol Trip help you plan each stay in Bangkok.
Frequently Asked Questions (FAQs)
How long does phalloplasty take, and how many surgeries are involved?
It depends on the technique. Some approaches are completed in a single operation; others, such as the two-stage forearm technique, are staged over several months. Your surgeon will outline the timeline that fits your chosen method during consultation.
Will I be able to father children after phalloplasty?
Phalloplasty doesn’t affect fertility on its own, but many patients have already had a hysterectomy or oophorectomy beforehand, which does. If preserving fertility matters to you, discuss options such as egg freezing with your care team before surgery.
How much sensation will I have afterward?
This varies by technique — the radial forearm flap generally offers the best sensation, while others trade some sensitivity for a less visible donor site. We’ll walk you through the differences so you can choose the flap that best matches your priorities.
Should I choose phalloplasty or metoidioplasty?
It depends on your priorities. Phalloplasty creates a larger penis that can be used for penetration with an implant, but it involves several operations, a donor-site scar and a higher risk of urethral complications. Metoidioplasty creates a smaller penis from your own clitoral tissue, with natural erections and usually just one operation. Some patients have metoidioplasty first and phalloplasty later.
Will I be able to have penetrative sex?
Yes, in most cases, once a penile implant is placed. The implant is usually added about 1–2 years after phalloplasty, when sensation has returned so you can feel any pressure on the penis. See Penile Implants.
Do I have to have my urethra lengthened?
No. Urethral lengthening allows you to stand to urinate, but it carries the highest risk of complications, such as leaks and narrowing. Many patients choose phalloplasty without urethral lengthening, or with partial lengthening, for a simpler operation and fewer complications.
What will the donor site look like?
It depends on the technique. With ALT, the thigh is covered with a skin graft from the other thigh and can be hidden by shorts. A forearm scar is visible, while groin and back scars are easier to conceal. Your surgeon will show you examples at consultation.
How long should I stay in Bangkok after phalloplasty?
Plan to stay in Bangkok for about 4–6 weeks after the main phalloplasty operation. This covers your hospital stay, daily wound care while the flap heals, and catheter removal after about 3 weeks. Earlier and later stages need shorter stays, and you’ll usually return several times. Thailand is one of the world’s most experienced destinations for gender-affirming surgery, and Kamol Trip can arrange accommodation close to the hospital.






